

Peptides are defined as short amino acid chains that function as molecular tools in diagnostics, enabling precise detection of disease through biomarkers, imaging probes, and biosensors. Understanding how peptides are used in diagnostics matters because their small size, tunable binding specificity, and superior tissue penetration give them clear advantages over traditional antibody-based probes. Researchers working in oncology, infectious disease, and metabolic research now rely on peptide-based assays to detect targets that conventional methods miss. Standards like CA19-9 integration and ELISA-based immunoassays have already demonstrated the clinical value of peptide applications in diagnostics, and the pace of development in 2026 makes this one of the most consequential areas in translational medicine.
How are peptides used in diagnostics?
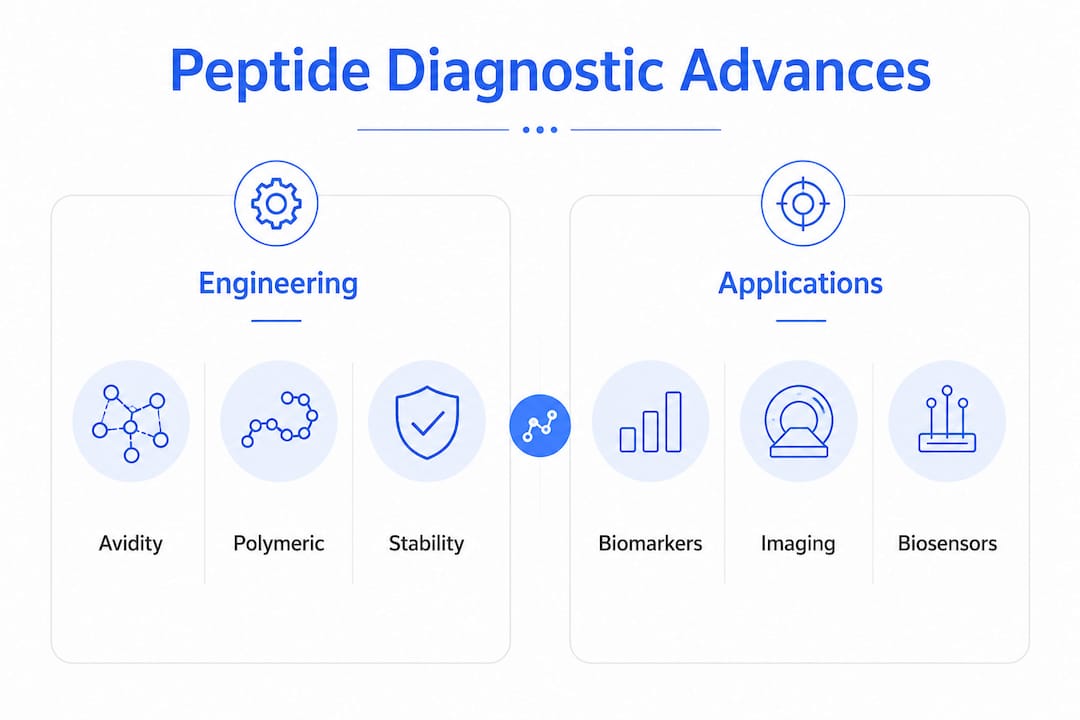
Peptides serve three primary diagnostic roles: molecular biomarkers, imaging agents, and biosensor components. Each role exploits a different property of peptide chemistry, and together they cover a wide spectrum of clinical applications.
As biomarkers, peptides appear in blood, urine, and tissue samples at concentrations that reflect disease state. Liquid biopsy platforms use peptide signatures to detect cancer-associated protease activity without requiring tissue extraction. Immunoassays built around synthetic peptides identify antibodies against specific pathogens, as demonstrated in SARS-CoV-2 serology testing.
As imaging agents, peptides act as molecular probes that bind selectively to disease-associated receptors. Radiolabeled peptides targeting integrin αvβ6 and annexin A2 are used in PET and SPECT imaging to visualize tumor margins and metastatic spread. Peptide-based in vivo imaging has also shown strong results in ophthalmology, particularly for early detection of diabetic retinopathy, where peptides act as linkers that translate molecular recognition into a readable optical signal.

As biosensor components, peptides connect molecular recognition events to measurable outputs. Synthetic bicyclic peptides, for example, enable ultrasensitive immunoassays at ultralow biomarker concentrations, offering a cost-effective alternative to antibodies in high-throughput point-of-care devices.
Key diagnostic roles peptides fill today include:
- Serum biomarker detection in cancer and metabolic disease panels
- Receptor-targeted imaging probes for PET, SPECT, and MRI
- Biosensor recognition elements in lateral flow and electrochemical assays
- Protease activity sensors in cancer liquid biopsy
- Antigen mimics in infectious disease serology
Pro Tip: When selecting a peptide for a biosensor application, prioritize sequences with demonstrated binding affinity in the target biological matrix, not just in buffer. Matrix effects in serum or plasma can reduce apparent affinity by an order of magnitude.
Peptides outperform antibodies as diagnostic probes because of their smaller size, lower chemical modification cost, and better tissue penetration. This makes them especially valuable for early-stage cancer detection, where sensitivity at low biomarker concentrations determines clinical utility.
How do advances in peptide engineering improve diagnostic sensitivity?
Peptide engineering has moved well beyond simple sequence optimization. The two most impactful advances in 2026 are avidity enhancement through polymeric peptide structures and user-defined peptide libraries for mass spectrometry-based diagnostics.
Avidity engineering and polymeric peptides
Monomeric peptides bind a single target site. Polymeric peptides present multiple binding units on a single scaffold, dramatically increasing the effective affinity through avidity. Avidity-enhanced polymeric peptides achieved a 218% avidity gain compared to their depolymerized counterparts. That gain translates directly into higher ELISA signal-to-noise ratios and lower detection thresholds, which matters most when biomarker concentrations are near the assay’s limit of detection.
| Parameter | Monomeric peptide | Polymeric/engineered peptide |
|---|---|---|
| Binding avidity | Single-site | Multivalent, 218% gain |
| ELISA sensitivity | Baseline | Significantly improved |
| Protease stability | Moderate | Enhanced via cyclization |
| Cost per assay | Low | Moderate |
| Tissue penetration | High | High |
User-defined peptide libraries
Pepyrus, a user-defined peptide library platform, recovers more than 75% of expected peptide sequences per injection and detects known neoantigens at 0.1 fmol. Libraries exceeding 10,000 peptides per run enable personalized mass spectrometry diagnostics that identify patient-specific cancer antigens. This level of sensitivity opens the door to neoantigen-based liquid biopsy at earlier disease stages than previously achievable.
Peptide stability remains the most persistent engineering challenge. Proteolytic enzymes in biological samples degrade linear peptides rapidly, producing false negatives in assays that depend on intact sequence recognition. Structural modifications such as cyclization and incorporation of non-natural amino acids protect against enzymatic degradation without sacrificing binding specificity. Researchers working with in vitro diagnostic assays should treat stability testing in the target matrix as a mandatory validation step, not an optional one.
Pro Tip: Incorporate D-amino acid substitutions at protease-susceptible positions early in your peptide design cycle. Waiting until late-stage validation to address stability issues adds significant time and cost to assay development.
What are notable clinical applications of peptides in diagnostics?
The clearest evidence for the diagnostic use of peptides comes from oncology and infectious disease research, where clinical data now supports their integration into standard workflows.
-
Pancreatic cancer screening. Integrating peptide-based biomarkers with CA19-9 raises diagnostic AUC to 0.961, a meaningful improvement over CA19-9 alone. Pancreatic cancer carries a 5-year survival rate of 13.3%, making early detection the single most important factor in patient outcomes. Peptide panels that complement CA19-9 address the marker’s known limitations in early-stage disease.
-
SARS-CoV-2 serology. Avidity-enhanced polymeric peptides in an ELISA format achieved sensitivity of 95.01% and specificity of 100% for SARS-CoV-2 antibody detection. Those figures meet or exceed the performance of many antibody-based assays, at lower production cost and with greater batch-to-batch consistency.
-
Diabetic retinopathy imaging. Peptides with tunable structures function as molecular imaging linkers in real-time in vivo imaging of retinal vasculature. Early detection of retinal changes before symptom onset is the primary clinical goal, and peptide probes offer the specificity needed to distinguish pathological from normal tissue.
-
Cancer liquid biopsy via nanosensors. High-throughput nanosensor arrays use peptide substrates to detect protease activity patterns in plasma. Different cancers express distinct protease signatures, so multiplexed peptide panels can classify tumor type and stage from a single blood draw.
-
Neoantigen identification. Personalized peptide libraries combined with mass spectrometry and bioinformatics pipelines identify patient-specific neoantigens for both diagnostic classification and immunotherapy target selection. This multi-omics approach represents the current frontier of precision oncology diagnostics.
The role of peptides in rare disease detection follows the same principles. Researchers working in that space can find parallel frameworks in peptide diagnostics for rare diseases, where biomarker scarcity makes peptide sensitivity especially critical.
What challenges and future directions exist for peptide diagnostics?
Peptide diagnostics face three categories of challenge: stability, validation scale, and off-target effects. Each has a defined mitigation path, but none is fully solved.
- Proteolytic degradation in plasma and tissue reduces assay sensitivity. Cyclization and non-natural amino acid incorporation are the primary solutions, but they add synthesis complexity and cost.
- Cohort diversity in validation studies remains limited. Most published peptide diagnostic studies use single-center cohorts, which restricts generalizability across ethnic and metabolic backgrounds.
- Off-target binding in imaging probe applications can generate false-positive signals in tissues with high non-specific peptide uptake. Careful sequence optimization and blocking strategies reduce but do not eliminate this risk.
- Regulatory pathways for peptide-based in vitro diagnostics are still evolving. Researchers should track guidance from the FDA’s Center for Devices and Radiological Health and Health Canada’s Medical Devices Directorate as frameworks develop.
- Data integration is the most underappreciated challenge. Peptide biomarker panels generate large, high-dimensional datasets that require bioinformatic pipelines to interpret meaningfully.
Machine learning addresses the data integration problem directly. Combining peptide biomarker panels with machine learning and clinical metadata reaches AUC values above 0.96 in cancer screening, outperforming any single-marker test. That performance gain comes from the algorithm’s ability to weight each peptide’s contribution based on patient-specific clinical context.
Pro Tip: Build your bioinformatic pipeline before you finalize your peptide panel. Retrofitting an analysis framework to an existing dataset almost always reveals gaps in the experimental design that require additional sample collection.
Key Takeaways
Peptides deliver their highest diagnostic value when engineering advances, clinical validation, and bioinformatic integration are treated as a single coordinated workflow rather than sequential steps.
| Point | Details |
|---|---|
| Peptides outperform antibodies | Smaller size and lower cost make peptides superior probes for early-stage disease detection. |
| Avidity engineering multiplies sensitivity | Polymeric peptides achieve a 218% avidity gain, directly improving ELISA signal-to-noise ratios. |
| Clinical AUC reaches 0.961 | Combining peptide biomarkers with CA19-9 sets a new benchmark for pancreatic cancer screening accuracy. |
| Stability requires active management | Cyclization and non-natural amino acids are mandatory for reliable assay performance in biological matrices. |
| Machine learning amplifies panel performance | Integrating peptide data with clinical variables and AI algorithms pushes cancer screening AUC above 0.96. |
Why peptide diagnostics deserve more attention than they get
Peptide diagnostics sit in an unusual position in translational research. The underlying science is mature enough to produce AUC values above 0.96 in cancer screening, yet clinical adoption lags behind what the data justifies. I think the gap exists because most researchers treat peptide selection, assay engineering, and data analysis as separate problems handled by separate teams. That siloed approach consistently underperforms.
The researchers making the most progress are those who design the peptide sequence, the assay format, and the analysis pipeline simultaneously. Avidity engineering is a good example. A polymeric peptide that delivers a 218% avidity gain only produces better clinical outcomes if the assay format and detection threshold are designed to exploit that gain. A standard ELISA protocol built for monomeric peptides will not capture the full benefit.
The other thing I’ve observed is that stability testing gets treated as a late-stage checkbox rather than an early design constraint. Peptides that perform well in buffer fail in plasma because no one tested them in the actual matrix during sequence optimization. That single oversight accounts for a disproportionate share of failed assay validations.
The future of peptide diagnostics is multiplexed, personalized, and AI-assisted. Researchers who build those three elements into their workflow from the start will produce results that translate to the clinic. Those who bolt them on afterward will keep publishing promising preliminary data without clinical follow-through.
— Admin
Peptilab supports your peptide diagnostic research
Researchers building peptide-based diagnostic assays need materials that meet the same standards their data does.
Peptilab supplies research-grade peptides with verified purity above 99%, each accompanied by a certificate of analysis from third-party testing. The catalog covers peptides relevant to metabolic research, oncology biomarker studies, and biosensor development, with Canadian fulfillment that eliminates import delays. Researchers who need to understand the full scope of peptide types available for diagnostic work can start with Peptilab’s scientific peptide guide. For those working at the intersection of peptide diagnostics and rare disease detection, the rare disease peptide research guide provides a practical framework for biomarker selection and assay design.
FAQ
What makes peptides effective as diagnostic biomarkers?
Peptides offer high target specificity, small molecular size, and tunable binding affinity, making them detectable at low concentrations in complex biological matrices like plasma and urine.
How do peptides compare to antibodies in diagnostic assays?
Peptides outperform antibodies in tissue penetration, chemical modification cost, and batch consistency. Synthetic bicyclic peptides achieve ultrasensitive detection at ultralow biomarker concentrations.
What is avidity engineering in peptide diagnostics?
Avidity engineering creates multivalent peptide structures that bind multiple target sites simultaneously. Polymeric peptides produced through this method show a 218% avidity gain over monomeric forms, directly improving assay sensitivity.
How does machine learning improve peptide-based diagnostics?
Machine learning algorithms combine peptide biomarker panels with clinical metadata to discriminate disease states more accurately than any single marker. Integrated models reach AUC values above 0.96 in cancer screening applications.
What is the biggest technical challenge in peptide diagnostic development?
Proteolytic degradation in biological samples is the primary challenge. Cyclization and non-natural amino acid substitutions are the most effective structural solutions for maintaining assay reliability in clinical matrices.