

Therapeutic peptide categories are defined as groupings of bioactive peptides organized by their primary mechanism of action and clinical application. With over 80 FDA-approved peptide therapeutics as of 2024, the field spans functions from metabolic regulation to tissue repair to cosmetic skin rejuvenation. The Peptide Association’s 12-category classification framework grades peptides by evidence strength, giving researchers and clinicians a structured way to evaluate confidence levels across types. Understanding these categories matters because many peptides are pleiotropic, meaning a single compound can act across multiple biological systems. This article maps the main functional categories, their mechanisms, and their applications in both medical and cosmetic research.
What are the main therapeutic peptide categories and how do they work?

Therapeutic peptide classifications are built primarily on mechanism of action, not molecular size or origin. This approach reflects how peptides actually behave in biological systems, where receptor binding, signaling cascade activation, and tissue-level effects define clinical utility. Researchers and clinicians who understand these mechanisms can predict cross-category behavior and interpret study findings with greater accuracy.
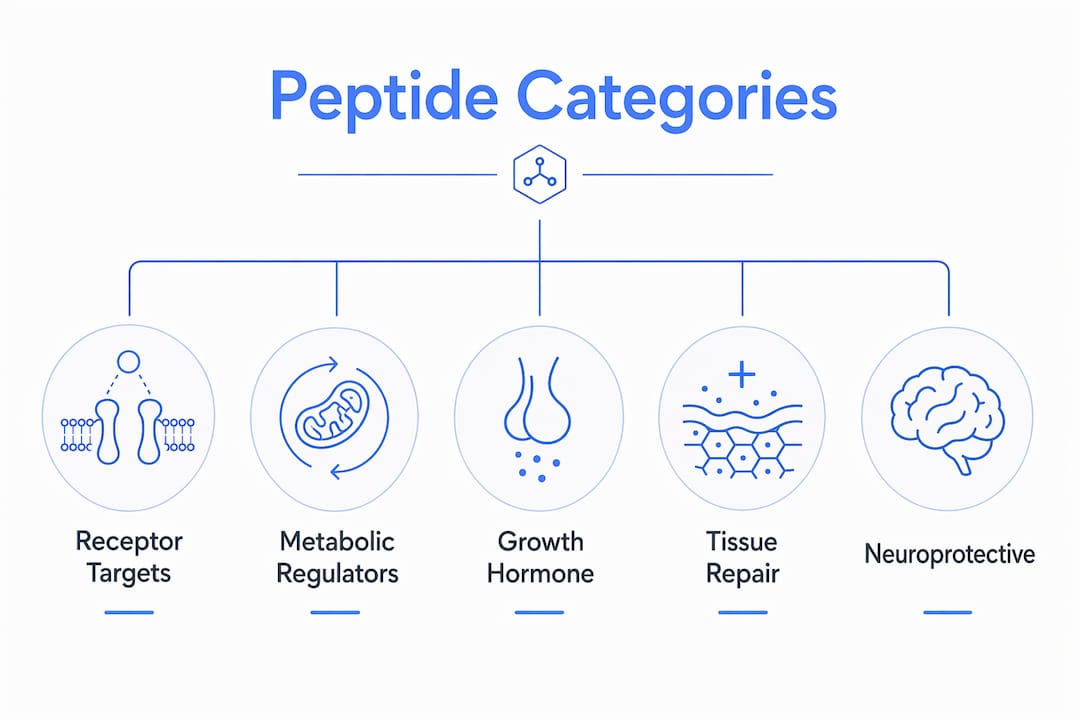
The major functional categories include:
- GLP-1 receptor agonists: Peptides like semaglutide bind glucagon-like peptide-1 receptors to regulate insulin secretion, slow gastric emptying, and reduce appetite. These are among the most clinically validated peptide types, with strong evidence from large randomized controlled trials.
- Growth hormone secretagogues (GHS): Compounds like CJC-1295 and ipamorelin stimulate the pituitary to release growth hormone. They are used in research on body composition, recovery, and aging.
- Tissue repair and regenerative peptides: BPC-157 and TB-500 (thymosin beta-4) promote angiogenesis, collagen synthesis, and cellular migration. These peptides appear in both wound healing and musculoskeletal recovery research.
- Antimicrobial peptides (AMPs): These disrupt bacterial membranes directly, offering a mechanism distinct from conventional antibiotics. Defensins and cathelicidins are well-studied examples.
- Neuroprotective peptides: Compounds like Semax and Selank modulate brain-derived neurotrophic factor (BDNF) and related pathways. Research interest centers on cognitive function, anxiety, and neurodegeneration.
- Immune-modulating peptides: Thymosin alpha-1 regulates T-cell activity and has been studied in oncology and chronic infection contexts.
- Cosmetic and skin-targeting peptides: GHK-Cu (copper peptide) stimulates collagen production and has antioxidant properties. Matrixyl (palmitoyl pentapeptide-4) is another widely studied example in anti-aging formulations.
Endogenous peptide hormones differ significantly from synthetic therapeutic peptides in their physiological pathways. Confusing the two creates real risk in research design and clinical interpretation. Mechanism-based classification resolves this by anchoring each peptide to its specific receptor target and downstream effect.
Pro Tip: When a peptide appears in multiple category lists, check its primary receptor target first. That target defines its dominant mechanism and the most relevant evidence base for your application.
How does evidence grading apply across peptide therapy categories?
Evidence grading is the second axis of therapeutic peptide classification, and it determines how much clinical confidence a category carries. The Peptide Association’s 12-category framework assigns one of four evidence grades to each category: Strong, Moderate, Limited, and Emerging.
Here is how those grades map to familiar categories:
- Strong evidence: GLP-1 receptor agonists and FDA-approved GH secretagogues. These categories have large randomized controlled trials, regulatory approval from the FDA and EMA, and well-characterized safety profiles.
- Moderate evidence: Tissue repair peptides like BPC-157 have promising preclinical data and early human studies, but lack the large-scale RCT data required for regulatory approval.
- Limited evidence: Neuroprotective peptides such as Semax have regional approvals (Russia, Eastern Europe) but limited Western regulatory review.
- Emerging evidence: Mitochondrial peptides like MOTS-c represent a newer category with compelling mechanistic rationale but early-stage human data only.
Regulatory status tracks closely with evidence grade. Only therapeutic peptides are strictly regulated by agencies like the FDA and EMA, while cosmetic peptides operate under a lighter regulatory framework. This divergence matters for researchers sourcing peptides for specific study designs.
Pro Tip: Cross-reference a peptide’s evidence grade with its regulatory status before designing a study protocol. A peptide with “moderate” evidence may have strong preclinical data but no approved human dosing guidelines, which changes your safety assessment entirely.
The evidence grading system also prevents a common error: treating all peptides within a functional category as interchangeable. GLP-1 agonists approved by the FDA carry a fundamentally different evidence weight than a novel GLP-1 analog still in phase 1 trials. The 12-category framework makes that distinction explicit and traceable.
What are the applications of therapeutic peptides across medical and cosmetic fields?
Therapeutic peptide applications span a wider range than most researchers initially expect. The same biological mechanisms that drive metabolic regulation in one context can influence skin aging in another. The table below maps major categories to their primary applications and key peptide examples.
| Category | Primary application | Key peptide examples |
|---|---|---|
| Metabolic regulators | Diabetes, obesity, weight management | Semaglutide, tirzepatide |
| Growth hormone secretagogues | Body composition, recovery, anti-aging | CJC-1295, ipamorelin, GHRP-6 |
| Tissue repair and regeneration | Wound healing, musculoskeletal recovery | BPC-157, TB-500 |
| Neuroprotective | Cognitive function, anxiety, neurodegeneration | Semax, Selank, dihexa |
| Immune modulation | Oncology support, chronic infection | Thymosin alpha-1 |
| Cosmetic and skin-targeting | Anti-aging, collagen synthesis, skin repair | GHK-Cu, Matrixyl, argireline |
| Antimicrobial | Infection resistance, wound protection | Defensins, LL-37 |
Metabolic peptides represent the most clinically advanced category. Dual-agonist GLP-1 and GIP treatments achieve 15–18% weight reduction in clinical trials, outperforming single-pathway drugs. That result reflects the additive benefit of co-activating two distinct metabolic receptors simultaneously.
Cosmetic peptides occupy a unique position in this classification. GHK-Cu, for example, stimulates collagen and elastin synthesis, reduces inflammation, and shows antioxidant activity. It appears in both regenerative medicine research and topical skincare formulations. This crossover is common among pleiotropic peptides and requires application-specific evaluation rather than a single fixed category label.
- Metabolic research benefits from combination approaches, with dual-agonist peptides showing superior outcomes over monotherapy.
- Regenerative peptides like BPC-157 are studied for both systemic healing and localized tissue repair.
- Cosmetic peptides like argireline (acetyl hexapeptide-3) inhibit neuromuscular signaling to reduce expression lines, a mechanism borrowed from neurotoxin pharmacology.
- Neuroprotective peptides are gaining traction in longevity research, particularly those targeting BDNF upregulation.
What are the challenges in classifying therapeutic peptides by category?
Classification of therapeutic peptides is not a clean exercise. Several structural and biological features create genuine ambiguity that researchers must account for when interpreting category labels.
Pleiotropy is the central challenge. Peptides like BPC-157 act across tissue repair, anti-inflammatory, and even neuroprotective pathways simultaneously. Placing BPC-157 in a single category misrepresents its biology. The correct approach is to classify it by the application under study, not by a fixed universal label.
Immunogenicity and stability add another layer of complexity. Therapeutic peptides offer high specificity compared to small molecules, but they face real clinical hurdles: immune responses to exogenous peptides, rapid enzymatic degradation in vivo, and impurity control during synthesis. These factors affect not just safety but also how a peptide behaves across different biological contexts, which in turn affects category assignment.
Key classification challenges researchers encounter include:
- Overlapping mechanisms: A peptide may agonize multiple receptor subtypes, making single-category assignment misleading.
- Endogenous vs. synthetic distinctions: Synthetic analogs of endogenous peptides often have modified half-lives or receptor selectivity that shifts their functional category relative to the natural compound.
- Regulatory gray zones: Cosmetic peptides and research-grade peptides operate in different regulatory environments than FDA-approved therapeutics, which affects how evidence grades translate to practice.
- Emerging categories: Mitochondrial peptides and epigenetic-targeting peptides are accumulating preclinical data faster than regulatory frameworks can accommodate them.
Pro Tip: When evaluating a peptide for research use, document its primary receptor target, its evidence grade, and its regulatory status as three separate data points. Treating these as one combined judgment leads to errors in study design and safety assessment.
The peptide compatibility considerations around stability and formulation also influence how a peptide is categorized in practice. A compound that degrades rapidly under physiological conditions may require a delivery modification that changes its effective mechanism, which can shift its functional classification in a research context.
Key Takeaways
Therapeutic peptide categories are defined by mechanism of action and evidence grade, and understanding both axes is the foundation of rigorous peptide research and clinical application.
| Point | Details |
|---|---|
| Mechanism-based classification | Categories are defined by receptor targets and biological effects, not molecular size alone. |
| 12-category evidence framework | The Peptide Association grades peptides from Strong to Emerging, directly linking category to clinical confidence. |
| Pleiotropy requires context | Peptides like BPC-157 span multiple categories; classify by the specific application under study. |
| Regulatory status varies by use | FDA and EMA regulate therapeutic peptides strictly; cosmetic peptides face lighter oversight. |
| Dual-agonist metabolic peptides lead | GLP-1/GIP co-activation achieves 15–18% weight reduction, the strongest clinical result in the metabolic category. |
Why mechanism-based classification changed how I read peptide research
The first time I encountered a study on BPC-157 listed under three different category headings in three separate papers, I assumed the authors were being sloppy. They were not. They were reflecting a genuine biological reality that the field had not yet built consistent language around.
Mechanism-based classification with evidence grading is not just an academic exercise. For anyone designing a study or evaluating a peptide for a specific application, knowing whether you are working with a Strong-evidence compound or an Emerging-evidence compound changes every downstream decision, from dosing rationale to safety monitoring to how you frame your conclusions.
The part that most classification guides underemphasize is the regulatory gray zone. Cosmetic peptides and research-grade peptides are not held to the same standard as FDA-approved therapeutics, and that gap is wider than most researchers assume. Purity, impurity profiling, and certificate of analysis documentation become the practical substitutes for regulatory oversight in those contexts.
The future of peptide classification will likely move toward multi-axis systems that capture mechanism, evidence grade, and delivery format simultaneously. The current framework is a strong foundation. Researchers who internalize it now will be better positioned as the field adds more categories and more compounds.
— Admin
Peptilab’s research-grade peptide catalog by category
Researchers who understand therapeutic peptide categories need a supply source that organizes products the same way.
Peptilab carries research-grade peptides across metabolic, regenerative, cosmetic, and neuroprotective categories, each verified at greater than 99% purity and accompanied by third-party certificates of analysis. Every product page links to its COA, so you can confirm identity, purity, and impurity profile before committing to a study design. Researchers focused on metabolic applications can browse metabolic research peptides directly, while those working in skin and anti-aging research will find a dedicated cosmetic peptide catalog organized by mechanism. Canadian fulfillment means no import delays and no customs uncertainty for domestic research teams.
FAQ
What are the main therapeutic peptide categories?
The main categories are metabolic regulators, growth hormone secretagogues, tissue repair peptides, neuroprotective peptides, immune-modulating peptides, antimicrobial peptides, and cosmetic peptides. Each category is defined by its primary receptor target and mechanism of action.
How does the Peptide Association’s 12-category system work?
The framework grades peptides by evidence strength: Strong (large RCTs and FDA approval), Moderate, Limited, and Emerging. This grading helps researchers and clinicians assess how much clinical confidence a given peptide category carries.
What makes a peptide pleiotropic?
A pleiotropic peptide acts on multiple receptor systems or biological pathways simultaneously. BPC-157 is a well-known example, showing activity in tissue repair, anti-inflammatory, and neuroprotective contexts depending on the application studied.
How do cosmetic peptides differ from therapeutic peptides?
Cosmetic peptides and therapeutic peptides often share biological mechanisms, but only therapeutic peptides are strictly regulated by agencies like the FDA and EMA. Cosmetic peptides operate under lighter regulatory oversight, making purity documentation and third-party testing especially important.
What is the strongest evidence category for peptide therapeutics?
GLP-1 receptor agonists hold the strongest evidence grade, supported by large randomized controlled trials and FDA approval. Dual-agonist GLP-1 and GIP treatments achieve 15–18% weight reduction in clinical trials, representing the most clinically validated outcome in the metabolic peptide category.